


April 1, 2026
 Shedding Light on the Risks
& Benefits of Medications
Click the dates to jump to more details.
Independent reporting on drug recalls, medication safety and integrative health, including supplements. No pharma funding.
To help you sort through the news on the COVID-19 vaccine’s progress, MedShadow has created the MedShadow Vaccine Tracker, the only tracker focused on the side effects and adverse events associated with proposed COVID-19 vaccinations.
Rather than injecting patients with a weakened virus or proteins from the pathogen that our immune systems can recognize, which is what’s typically done when we get a flu vaccine, the new vaccines from Moderna and Pfizer — the two that made it to the market first in the U.S. — contain mRNA (messenger RNA), which is a genetic template that instructs our cells to build the viral proteins that our immune systems can then recognize. Its main perk is that allowing our bodies to produce the proteins (rather than growing them in a lab like traditional vaccines) slashes production time. For nearly 20 years, researchers have been interested in using mRNA in vaccines; and some were even tested in early clinical trials for rabies, influenza and Zika. However, the vaccines for COVID-19 will be the first mRNA vaccines ever authorized by the FDA.
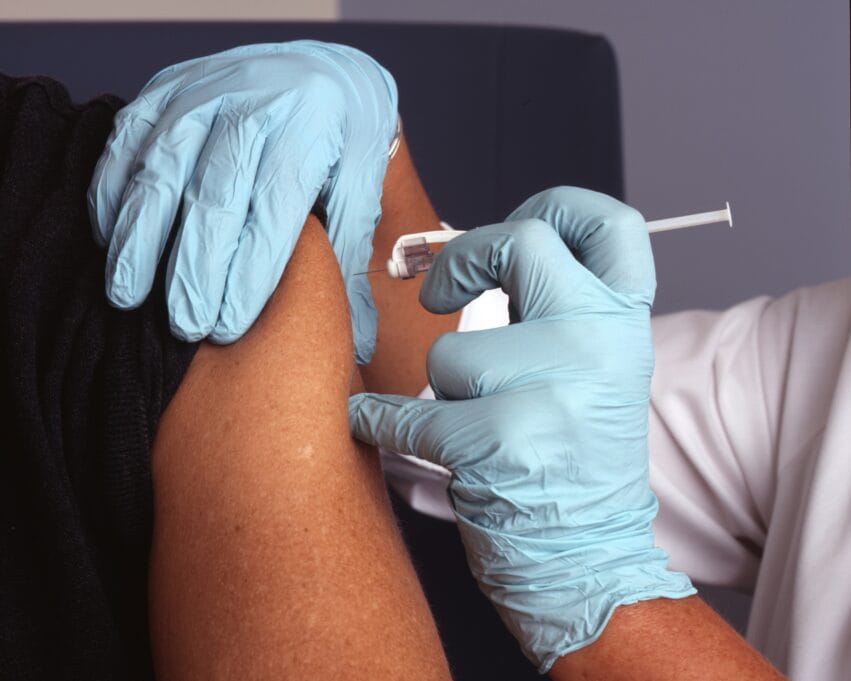
Some risks and minor side effects, such as a sore arm where the vaccine is injected or a light skin rash, are clearly worth the benefit of being protected against a disease. Where to draw the line at what is or is not acceptable is a personal decision. That’s where the MedShadow Vaccine Tracker can help.
On the tracker, we will be publishing up-to-date Phase 3 results information about the risks of each vaccination. Phase 3 tests the vaccine for safety and efficacy in large groups of people (tens of thousands) and is the last stage before the FDA considers approval for use in the population at large. We continue following verified reports as the vaccines are offered to the general public. It is important to note that reports of events occurring after vaccination are not inherently linked to it. As countries begin to vaccinate hundreds of millions of people, some would inevitably be diagnosed with illnesses or pass away each day with or without the injections.
Jump to:
Moderna | Pfizer | CanSinBio (China) | Gameleya (Russia) | Johnson & Johnson
Astrazeneca | Novavax (UK) | Sinopharm (China) | Sinovac (China) | Murdoch (England)|Bharat Biotech
Moderna started Phase III clinical trials for its vaccine candidate in July. In earlier trials, nearly half of patients experienced common adverse effects like injection site pain, rash, headaches, muscle soreness, nausea and fevers after the second injection. These effects generally subsided within two days. CNBC spoke to a few individuals, some participating in Moderna’s trial and some in Pfizer’s trial who said much the same thing: the side effects were intense and included a high fever, body aches, bad headaches and exhaustion, but were worth it for protection from Covid-19.
In the FDA report published in December, the most common side effects were pain at injection site (91.6% of patients), fatigue (68.5%), headache (63.0%), muscle pain (59.6%), joint pain (44.8%), and chills (43.4%). Three patients experienced Bell’s Palsy, a sudden, and usually temporary, weakening or paralysis of the facial muscles.
The CDC reports that 11% of patients experienced swollen lymph nodes after the first shot. That raised to 16% after the second shot.
A few patients with facial fillers experienced swelling after receiving the vaccine. They were treated with antihistamines and steroids.
January 18: In California, officials halted the use of one particular batch of Moderna vaccines (lot 41L20A) after a small cluster (fewer than 10) of patients at one particular site experienced allergic reactions that required medical attention.
February 1: A study posted on Feb 1 showed that patients who received the vaccine after having been previously infected with COVID-19 showed greater immune response to the first shot and more intense side effects that are associated with strong immune responses like fever and muscle aches. The study included patients who received either the Moderna or Pfizer vaccine. Some scientists believe these patients may only need a single shot to provide sufficient immunity, but more research is needed.
February 12: Out of the first 7.5 million doses administered from Dec 14- Jan 18, 19 cases of anaphylaxis were reported to VAERS after the Moderna vaccine. No patients have died from anaphylaxis. Patients are now being monitored for 15-30 minutes after receiving the vaccine to watch for signs of anaphylaxis. The CDC suggests that anyone who has an immediate allergic reaction to a single dose of an mRNA vaccine (Moderna or Pfizer) should not get the second dose. If your reaction was not immediate, you may be referred to an allergy specialist. The vaccines do not contain polysorbate, but do have a related ingredient, polyethylene glycol (PEG). If you have an allergy to either of these chemicals, you should not get the vaccines.
Many patients are reporting injection site reactions that show up shortly after the injection or up to a week later. These reactions — which are characterized by swelling, redness, itching, rashes, heat and pain — are expected to last a day to a week. Physicians emphasize that while these effects can be scary, they are not dangerous and should not prevent someone from getting the second shot. So far, doctors do not report seeing these reactions after the second shot, however so few have been given so far that scientists are not sure how common it will be on round two.
March 3: Allergy researchers at Mass General Hospital created a registry for healthcare professionals to report immediate and delayed reactions to COVID-19 vaccinations. On March 3, the researchers published a letter in the New England Journal of Medicine describing a series of 12 delayed injection site reactions including swelling and rashes. The researchers wrote that one patient received antibiotics although they were not necessary. Several others were treated with steroids or anti inflammatories. The letter included some photos and said that the reactions cleared up within a median of six days. Patients were encouraged to receive their second dose. Half of them did not experience the reaction the second time. A quarter did, but to a lesser degree.
March 8: Researchers from Mass General Brigham published a Research Letter in JAMA analyzing allergic reactions in employees who received their shots there. Out of 52,805 participants, 2.1% experienced some kind of allergic reaction, including hives, itching, rash, swelling or respiratory symptoms within the first three days after vaccination. Allergies were slightly more common with the Moderna vaccine than the Pfizer vaccine (2.2% compared to 1.95%). Sixteen experienced anaphylaxis.
Moderna has announced that it will begin testing its vaccine in children and adolescents, who they believe may have stronger immune responses, leading to more intense side effects.
April 20: Researchers have received over 25,000 responses to an online survey regarding menstrual changes after receiving any COVID-19 vaccine. The survey is ongoing as researchers hope to gain a better understanding of future directions of research. An op-ed in the New York Times explains how the vaccines could potentially interact with menstrual cycles, and why we really don’t know yet.
April 22: The CDC published an analysis of data from the first few months of voluntary V-safe surveys that suggested that the Moderna and Pfizer vaccines are safe for pregnant women. Pregnant patients self-reported slightly fewer side effects like fever, headache and chills than the general population, but more said they experienced nausea and injection site pain. Rates of adverse pregnancy outcomes such as pre-term birth were similar to rates seen before the pandemic. While promising, officials noted that more studies will be required.
April 26: MedShadow asked doctors about some of the unusual symptoms we’re hearing about in the comments: heart palpitations and visual disturbances. They hadn’t had patients who reported long-term symptoms, but said that if the symptoms occurred very quickly after vaccination, they could be related to allergic reactions or presyncope.
April 27: Clinical trials of Moderna and Pfizer vaccines showed 7 cases of Bell’s Palsy. An analysis published today in JAMA suggested the experience was no more frequent after these vaccines than other vaccines. It is unclear whether vaccines raise the risk of facial paralysis at all, but the authors write, “if an association between facial paralysis and mRNA COVID-19 vaccines exists, the risk is likely very low, as with other viral vaccines.”
May 5: Researchers published a detailed analysis of skin reactions after Moderna and Pfizer vaccinations, including swelling and rashes. Most patients with first dose reactions did not have reactions after their second dose. Larger reactions on the arm spreading outward from the injection site were the most common reactions among those who received the Moderna vaccine, followed by smaller localized reactions and hives. Five patients (1.9%) experienced a zoster (shingles) flare after the first dose but none after the second dose. About 1% of patients experienced a flare of an existing skin condition after each dose.
May 20: An analysis published in JAMA suggests that hearing loss is NOT a side effect of the Pfizer or Moderna vaccines.
June 10: The CDC says that as of May 31, VAERS had received 475 reports of myocarditis or pericarditis among people 30 years of age and younger who received a COVID-19 vaccine. Upon follow-up, the CDC and FDA confirmed 226 of the reports. They emphasize that more than 18 million people between ages 12-24 have received at least one dose of COVID-19 vaccine in the United States. A CDC Fact Sheet on the effect is available here.
June 23: About 1.9% of healthcare employees who received an mRNA vaccination had a skin reaction such as itching or a rash after the first dose. Most (83%) who reported a skin reaction after the first dose, did not experience it again after the second dose, according to a study today in JAMA Dermatology. Another 2.3% experienced a skin reaction after only the second dose.
August 18: The FDA and CDC authorized third shots for patients with specific conditions that compromise their immune systems. The Biden administration has also pushed for booster shots to be made available to everyone, eight months after their second dose, in response to waning antibody levels and a rise in breakthrough infections. People who took Pfizer, Moderna or J&J’s vaccines are still highly protected against hospitalization and death. This plan is not yet authorized. The agencies are also waiting for data to provide guidelines specific to J&J vaccine recipients in the coming weeks. Around a million people have gotten third shots so far in the US and abroad. The FDA hasn’t reviewed all of the data yet, but no new safety concerns have emerged thus far. See answers to frequently asked questions regarding the booster shots here.
August 19: The FDA and CDC are investigating the possibility that Moderna’s vaccine could be up to 2.5 times more likely to be associated with myocarditis (heart inflammation), especially for males under 30 years old. If true, the effect would still be exceedingly rare and scientists say the benefits still greatly outweigh the harms of vaccination. Most patients recover on their own with minimal intervention.
October 23:Researchers found that allergies to the mRNA vaccines are not likely due to the chemical PEG. Most patients (86.7%) who experienced an immediately allergic reaction after the first shot could safely receive the second dose if pretreated with antihistamines. None of the patients required hospital admission.
October 27: MedShadow reached out to cardiologist Jennifer Su, MD, to help you understand the risk of myocarditis in kids and teens who receive the COVID-19 vaccines. Read the article here.
Dec 8: The FDA authorized Astrazeneca’s monoclonal antibody treatment as an alternative to the vaccine for people over 12 years old who are immunocompromised or have a history of severe vaccine reactions. The treatment is given in two injections and protection is thought to last 6 months up to a year. It reduced the risk of symptomatic COVID-19 by 82%.
June 14: Researchers compared the adverse effects experienced by patients who took Pfizer or Moderna’s mRNA vaccine over the course of 42 weeks. The risk was very low for both, but those that took Pfizer’s were slightly more likely to suffer heart attacks or strokes. The researchers say there is a possibility that these outcomes are not linked to the vaccines, but to Covid infections, and that the results could also belie a slightly lower efficacy of Pfizer’s vaccine. They emphasize the benefits of both vaccines still outweigh the risks.
Feb 8, 2023: A booster shot of Moderna (the third shot, which is the same as the first two and is not the bivalent booster) was associated with spontaneously developing hives 8-13 days after the shot, that lasted six weeks or longer, according to a study in JAMA. The study suggested that 19-24 out of every 100,000 people vaccinated experienced the side effect.
July 3, 2023: Researchers are studying a possible link between vaccination and long COVID-like symptoms in a small minority of patients. These symptoms include experiences such as fatigue, irregular heart rates, and headaches that last for weeks after vaccination. Read more here.
Pfizer began Phase III clinical trial for its vaccine candidate in July. In earlier trials, some patients experienced common adverse effects like injection site pain, rash, headaches, muscle soreness, nausea and fevers. These effects generally subsided within two days. CNBC spoke to a few individuals, some participating in Pfizer’s trial and others in Moderna’s trial who said much the same thing: the side effects were intense and included a high fever body aches, bad headaches and exhaustion in addition to the more common side effects, but were worth it for protection from Covid-19.
Some patients described the side effects as being similar to a bad hangover. A nurse who participated in the clinical trial reported feeling minimal effects after the first dose, but a fever that reached more than 104 degrees Fahrenheit after the second injection, along with chills, headache, and intense injection site pain. According to researchers, her experience of having all symptoms together was rare, though many patients had one or two of these side effects. “Clinicians will need to be prepared to discuss with patients why they should trust the vaccine and that its adverse effects could look a lot like COVID-19,” the nurse wrote on Dec 7.
The FDA report published in December said the most common reactions were injection site reactions (84.1%), fatigue (62.9%), headache (55.1%), muscle pain (38.3%), chills (31.9%), joint pain (23.6%), fever (14.2%). Swollen lymph nodes occurred in 0.3% of patients. The FDA reported that four patients who received the vaccine experienced Bell’s Palsy.
January 12: A doctor in Florida died 16 days after receiving the vaccine from a rare blood disorder, acute immune thrombocytopenia. Both Pfizer and the CDC are investigating, though the company has released a statement that so far, they haven’t seen any signs in the clinical trials or data collected from early vaccinations that the death could be related to the vaccine. The blood disorder immune thrombocytopenia, has also been seen as a rare complication of COVID-19 itself, in both symptomatic and asymptomatic patients.
January 19: Twenty-three elderly patients in Norway died after receiving Pfizer’s vaccine. Officials are investigating whether or not the deaths are vaccine-related. Anthony Fauci, MD, director of the National Institute of Allergy and Infectious Diseases, suggests that while the deaths may be coincidental given the fragile population, it’s possible that side effects of the vaccines, like fevers, may have strained the frail patients’ bodies and contributed to their deaths. Norway has vaccinated about 45,000 people so far, most of whom live in nursing homes.
February 1: A study posted on Feb 1 showed that patients who received the vaccine after having been previously infected with COVID-19 showed greater immune response to the first shot and more intense side effects that are associated with strong immune responses like fever and muscle aches. The study included patients who received either the Moderna or Pfizer vaccine. Some scientists believe these patients may only need a single shot to provide sufficient immunity, but more research is needed.
February 12: Out of the first 9.9 million doses administered from Dec 14- Jan 18, 47 cases of anaphylaxis were reported to VAERS after the Pfizer vaccine. Patients are now being monitored for 15-30 minutes after receiving the vaccine to watch for signs of anaphylaxis. The CDC suggests that anyone who has an immediate allergic reaction to a single dose of an mRNA vaccine (Moderna or Pfizer) should not get the second dose. If your reaction was not immediate, you may be referred to an allergy specialist. The vaccines do not contain polysorbate, but do have a related ingredient, polyethylene glycol (PEG). If you have an allergy to either of these chemicals, you should not get the vaccines.
March 8: Researchers from Mass General Brigham published a Research Letter in JAMA analyzing allergic reactions in employees who received their shots there. Out of 52,805 participants, 2.1% experienced some kind of allergic reaction, including hives, itching, rash, swelling or respiratory symptoms within the first three days after vaccination. Allergies were slightly more common with the Moderna vaccine than the Pfizer vaccine (2.2% compared to 1.95%). Sixteen experienced anaphylaxis.
March 30: Researchers publish a case study of a single patient in which they suspect the Pfizer vaccine may have caused a rheumatoid arthritis flare. The flare was treated, and the patient is in remission. The researchers and RA advocacy groups still advise patients to get the vaccine as the benefits outweigh the risks of a flare up.
April 20: Researchers have received over 25,000 responses to an online survey regarding menstrual changes after receiving any COVID-19 vaccine. The survey is ongoing as researchers hope to gain a better understanding of future directions of research. An op-ed in the New York Times explains how the vaccines could potentially interact with menstrual cycles, and why we really don’t know yet.
April 22: The CDC published an analysis of data from the first few months of voluntary V-safe surveys that suggested that the Moderna and Pfizer vaccines are safe for pregnant women. Pregnant patients self-reported slightly fewer side effects like fever, headache and chills than the general population, but more said they experienced nausea and injection site pain. Rates of adverse pregnancy outcomes such as pre-term birth were similar to rates seen before the pandemic. While promising, officials noted that more studies will be required.
April 26: MedShadow asked doctors about some of the unusual symptoms we’re hearing about in the comments: heart palpitations and visual disturbances. They hadn’t had patients who reported long-term symptoms, but said that if the symptoms occurred very quickly after vaccination, they could be related to allergic reactions or presyncope.
April 27: Clinical trials of Moderna and Pfizer vaccines showed 7 cases of Bell’s Palsy. An analysis published today in JAMA suggested the experience was no more frequent after these vaccines than other vaccines. It is unclear whether vaccines raise the risk of facial paralysis at all, but the authors write, “if an association between facial paralysis and mRNA COVID-19 vaccines exists, the risk is likely very low, as with other viral vaccines.”
May 5: Researchers published a detailed analysis of skin reactions after Moderna and Pfizer vaccinations, including swelling and rashes. Nearly a quarter of patients had smaller local reactions after each of the two shots. Hives were the most common skin reaction (26% after the first shot, 18% after the second,) among patients who received the Pfizer vaccine. Several also experienced flares of existing skin conditions.
May 10: Pfizer’s vaccine received Emergency Use Authorization for 12 to 15-year-olds. The company reported that common adverse effects like chills and fever were more common in this age group than adults. Adverse reactions in adolescents 12 through 15 years of age included pain at the injection site (90.5%), fatigue (77.5%), headache (75.5%), chills (49.2%), muscle pain (42.2%), fever (24.3%), joint pain (20.2%), injection site swelling (9.2%), injection site redness (8.6%), lymphadenopathy (0.8%), and nausea (0.4%). These effects generally subsided within 1-2 days. While data on syncope (fainting) was not included, the announcement mentioned that fainting after vaccination is more common in teens than adults, and that safety measures should be in place to reduce this risk.
May 20: An analysis published in JAMA suggests that hearing loss is NOT a side effect of the Pfizer or Moderna vaccines.
May 23: The CDC is investigating reports of myocarditis in a small number of vaccinated teens. Myocarditis, or inflammation of the heart, has multiple causes but a viral infection is the most common trigger. In 2019, one million people were diagnosed with myocarditis, most of them under 40 years old. It’s not yet clear if these events were related to the vaccine.
June 9: A study in Nature Medicine suggests that there may be a very slightly elevated risk of blood disorders after receipt of the AstraZeneca vaccine, but NOT Pfizer’s. The study was based on an analysis of medical records in Scotland. Researchers say the vaccine’s benefits still outweigh the risks and that their results should not alter policy. The rates are similar to those seen with other common vaccines.
June 10: The CDC says that as of May 31, VAERS had received 475 reports of myocarditis or pericarditis among people 30 years of age and younger who received a COVID-19 vaccine. Upon follow-up, the CDC and FDA confirmed 226 of the reports. They emphasize that more than 18 million people between ages 12-24 have received at least one dose of COVID-19 vaccine in the United States. A CDC Fact Sheet on the effect is available here.
June 23: About 1.9% of healthcare employees who received an mRNA vaccination had a skin reaction such as itching or a rash after the first dose. Most (83%) who reported a skin reaction after the first dose, did not experience it again after the second dose, according to a study today in JAMA Dermatology. Another 2.3% experienced a skin reaction after only the second dose.
August 18: The FDA and CDC authorized third shots for patients with specific conditions that compromise their immune systems. The Biden administration has also pushed for booster shots to be made available to everyone, eight months after their second dose, in response to waning antibody levels and a rise in breakthrough infections. People who took Pfizer, Moderna or J&J’s vaccines are still highly protected against hospitalization and death. This plan is not yet authorized. The agencies are also waiting for data to provide guidelines specific to J&J vaccine recipients in the coming weeks. Around a million people have gotten third shots so far in the US and abroad. The FDA hasn’t reviewed all of the data yet, but no new safety concerns have emerged thus far. See answers to frequently asked questions regarding the booster shots here.
August 22: Researchers published two case studies of patients experiencing neurological effects such as losing balance and non-epileptic convulsions after the Pfizer and AstraZeneca vaccines. They emphasize that functional neurological disorders are treatable.
September 2: Researchers in Israel reviewed medical records of patients who had experienced Guillan-Barre Syndrome (GBS) prior to receiving Pfizer’s COVID-19 shot. Of the 579 patients, five were transferred to the hospital for neurological symptoms such as tremors or prickling sensations. Only one patient required medical care for relapse of GBS.
September 28: V-Safe data from 306 people who received their third shots showed that nearly identical numbers of patients reported side effects to the second and third shots. 79.4% and 74.1% reported local or systemic reactions, respectively, after the third dose compared to 77.6% and 76.5% who reported local or systemic reactions after the second dose, respectively.
October 23: Researchers found that allergies to the mRNA vaccines are not likely due to the chemical PEG. Most patients (86.7%) who experienced an immediately allergic reaction after the first shot could safely receive the second dose if pretreated with antihistamines. None of the patients required hospital admission.
October 27: MedShadow reached out to cardiologist Jennifer Su, MD, to help you understand the risk of myocarditis in kids and teens who receive the COVID-19 vaccines. Read the article here.
Dec 8: The FDA authorized Astrazeneca’s monoclonal antibody treatment as an alternative to the vaccine for people over 12 years old who are immunocompromised or have a history of severe vaccine reactions. The treatment is given in two injections and protection is thought to last 6 months up to a year. It reduced the risk of symptomatic COVID-19 by 82%.
Dec 31: CDC data shows that serious side effects of Pfizer’s shot are extremely rare in children 5-11. While many reported arm pain, fevers and muscle pain like the adults, only 11 out of more than 40,000 reported myocarditis. Seven of those have fully recovered and four are currently improving.
June 14: Researchers compared the adverse effects experienced by patients who took Pfizer or Moderna’s mRNA vaccine over the course of 42 weeks. The risk was very low for both, but those that took Pfizer’s were slightly more likely to suffer heart attacks or strokes. The researchers say there is a possibility that these outcomes are not linked to the vaccines, but to Covid infections, and that the results could also belie a slightly lower efficacy of Pfizer’s vaccine. They emphasize the benefits of both vaccines still outweigh the risks.
January 13, 2023: Prizer’s Omicron (bivalent) booster seemed to be associated with a heightened risk of stroke in patient 65 and older for three weeks after getting the shot, according to data from the Vaccine Safety Datalink, a federal safety surveillance system. The CDC and FDA released a joint statement that several other streams of data including: the Centers for Medicare and Medicaid Services database, The Vaccine Adverse Event Reporting System (VAERS), the Veteran’s Affairs (VA) database, and data from other countries did not show an association between the shot and strokes, and that they believe the vaccine is safe. Moderna’s Omicron (bivalent) booster did not show similar signals.
July 3, 2023: Researchers are studying a possible link between vaccination and long COVID-like symptoms in a small minority of patients. These symptoms include experiences such as fatigue, irregular heart rates, and headaches that last for weeks after vaccination. Read more here.
China granted the CanSinBio vaccine emergency approval prior to beginning a Phase III trial in August. In the Phase II trial, nearly three-quarters of patients reported at least one common mild adverse events including injection site pain, rash, headaches, muscle soreness, and fevers. Five people also reported vomiting.
Gamaleya Research Institute launched Phase III trials in August. But before they got started, President Putin announced that the vaccine was approved early, however, the Phase III trials are expected to continue. In the earlier trials, almost all of the patients experienced low-grade fevers. A small number of patients reported heart palpitations. Otherwise, reported side effects were similar to other vaccines and included injection site pain, rash, headaches, and muscle soreness.
Feb 2: The group reported efficacy data along with some data on side effects in The Lancet. The most common adverse events were flu-like illness (15.2% of those vaccinated) and local reactions (5.4% of those vaccinated).
The report also states that there were six grade 3 adverse events which were not associated with the vaccination: acute sinusitis, an exacerbation of urolithiasis along with renal colic and deep vein thrombosis (both associated with pre-existing comorbidities) and extremity abscess (due to physical injury and subsequent infection of the wound surface of the soft tissues of the finger).
Johnson & Johnson started a Phase III trial for its vaccine candidate in September 2020, but paused it on October 12 due to an unexplained illness and remains on hold. The company announced it would restart the trial on October 26. Pauses are common during clinical trials to evaluate specific adverse events, but the company has not shared details about the illness experienced by one of the trial volunteers. In earlier trials, about 70% of patients experienced at least one mild adverse effect similar to those seen with other vaccines, including injection site pain, rash, headaches, muscle soreness, and fevers.
On Feb 24, Johnson & Johnson shared data from its Phase III trials. The data suggested that while the vaccine is slightly less protective overall (but more protective against the 501Y.V2 variant that emerged from South Africa,) than the Moderna and Pfizer vaccines, it produced fewer side effects.
The report says the most common reactions were injection site reactions (50.2%), fatigue (38.2%), headache (38.9%), muscle pain (33.2%), nausea (14.2%) and fever (9.0%). Reactions were more common in patients under 60 than over 60.
Injection site pain lasted a median of 2 days, but up to 7 days in 2.3% of patients.
April 8: A vaccination site in Colorado paused operations after 11 patients became nauseous and dizzy minutes after receiving the Johnson & Johnson vaccine. Two patients were transmitted to the hospital, but the rest were deemed healthy enough to return home. Officials said that those vaccinated at the same site should not be concerned.
April 13: The U.S. is calling for a pause on distributing the Johnson & Johnson vaccine while the FDA and CDC investigate blood clots that occurred in six patients (out of 7 million who received the vaccine so far.) One patient died and another was hospitalized. All the clots occurred in women under 50 within two weeks of receiving the vaccine. The issue is similar to the one seen with the AstraZeneca vaccine in Europe.
April 20: Researchers have received over 25,000 responses to an online survey regarding menstrual changes after receiving any COVID-19 vaccine. The survey is ongoing as researchers hope to gain a better understanding of future directions of research.
April 23: The U.S. is resuming use of the vaccine after finding only 15 total cases of blood clots out of the 7 million vaccinated. Patients will be warned about the risk at vaccination sites. Symptoms including headache, leg pain and abdominal pain occur 6-14 days after vaccination. If you have these symptoms you should seek emergency medical treatment. It is treatable with certain blood thinners.
April 26: MedShadow asked doctors about some of the unusual symptoms we’re hearing about in the comments: heart palpitations and visual disturbances. They hadn’t had patients who reported long-term symptoms, but said that if the symptoms occurred very quickly after vaccination, they could be related to allergic reactions or presyncope.
April 27: Doctors suggested that patients with a history of immune-mediated thrombocytopenia, such as heparin-induced thrombocytopenia, should not get the Johnson and Johnson vaccine (mRNA vaccines like Pfizer and Moderna are ok). If you’re at an increased risk for other types of blood clots, (because you have obesity or you smoke, for example) you do not have an elevated risk of blood clots with the J&J vaccine.
April 30: Researchers published detailed data about 12 patients who experienced blood clots in JAMA.
May 13: The CDC has identified more cases of the rare clotting disorder associated with the J&J vaccine. The total is 28 cases. Three patients have died and four are still hospitalized. It’s more common in women than in men, and the benefits still outweigh the risks of vaccination, officials say. Nine million doses of the vaccine have been delivered in the U.S.
May 26: A 37-year old woman in Belgium died from a blood clot thought to be related to the Johnson and Johnson vaccine she received. The country has stopped using the vaccine in patients under the age of 41.
July 12: The FDA is attaching a warning to the Johnson & Johnson vaccine about a slightly elevated risk of developing Guillain-Barre syndrome, which can cause paralysis, within three weeks of receiving the vaccine. About 100 cases have been identified. Most patients recovered. One 57-year-old man died. The benefits still out weight the risks of vaccination, it says.
August 22: The FDA and CDC authorized third shots for patients with specific conditions that compromise their immune systems. The Biden administration has also pushed for booster shots to be made available to everyone, eight months after their second dose, in response to waning antibody levels and a rise in breakthrough infections. People who took Pfizer, Moderna or J&J’s vaccines are still highly protected against hospitalization and death. This plan is not yet authorized. The agencies are also waiting for data to provide guidelines specific to J&J vaccine recipients in the coming weeks. Around a million people have gotten third shots so far in the US and abroad. The FDA hasn’t reviewed all of the data yet, but no new safety concerns have emerged thus far. See answers to frequently asked questions regarding the booster shots here.
Dec 8: The FDA authorized Astrazeneca’s monoclonal antibody treatment as an alternative to the vaccine for people over 12 years old who are immunocompromised or have a history of severe vaccine reactions. The treatment is given in two injections and protection is thought to last 6 months up to a year. It reduced the risk of symptomatic COVID-19 by 82%.
Dec 16: The CDC’s vaccine advisors are meeting to review data that suggests a heightened risk of clotting disorders in patients who received the J&J vaccine. Women aged 30-49 appear to be the most affected, though the condition likely impacts 1 out of 100,000 vaccine recipients. Nine have died.
May 6: The FDA has limited the use of the J&J vaccine after 60 cases of blood clots associated with thrombocytopenia syndrome have been discovered. 18.7 million doses of the shot have been administered, and regulators don’t yet know who is at the highest risk of clots.
The vaccine has been approved for use in the U.K., Argentina, India, E.U. and Mexico, but in May 2024, the company stopped manufacturing the vaccine, citing low demand.
May 17, 2024: Astrazeneca is facing two lawsuits. One is a class action lawsuit from patients who experienced thrombosis after receiving the shot, and another is from a woman who was a clinical trial participant in the US. She says the company failed to support her after she suffered debilitating vaccine side effects such as nerve damage and double vision.
March 11: Denmark has paused the use of the AstraZeneca vaccine while it investigates whether it is responsible for blood clots — one fatal — in some patients.
“It is important for us that the citizens are confident in the offer we give them and trust that we can vouch for the quality of the vaccines we have in our program. Therefore, we react promptly until we have investigated whether there is a connection between the vaccine and the possible side effects ,” officials wrote in a press release.
March 15: Several other countries (Iceland, Norway, Denmark, Ireland, the Netherlands, Italy, France and Germany) have also paused use of the vaccine while unusual clotting events are investigated. Meanwhile, Thailand, which paused its use on Friday, March 12 restarted it on Sunday, March 14. On Sunday, AstraZeneca released a statement that its own review revealed “no increased risk” of clotting issues with the vaccine and that “So far across the EU and UK, there have been 15 events of DVT [deep vein thrombosis] and 22 events of pulmonary embolism reported among those given the vaccine, based on the number of cases the Company has received as of 8 March. This is much lower than would be expected to occur naturally in a general population of this size and is similar across other licensed COVID-19 vaccines.”
March 18: The European Medicines Agency (EMA) issued a statement that the benefits of the AstraZeneca vaccine outweigh the risks. The vaccine is not associated with an overall risk of blood clots, though there may be a very small increased risk of certain types of clots. The statement reads, “These are rare cases – around 20 million people in the UK and EEA had received the vaccine as of March 16 and EMA had reviewed only 7 cases of blood clots in multiple blood vessels (disseminated intravascular coagulation, DIC) and 18 cases of CVST [clots in the vessels that drain blood from the brain.] A causal link with the vaccine is not proven, but is possible and deserves further analysis.” These cases were more common in women under the age of 55. Germany, France, Italy, Latvia, Bulgaria and Slovenia have all stated that they’d restart or continue to offer the AstraZeneca vaccine in light of the news.
April 7: The EMA still says the benefits of the vaccines outweigh the risks. However, the group has suggested that blood clots be listed as a possible, albeit rare, side effect of the injection and that both patients and doctors be aware of the signs which include: shortness of breath, chest pain, leg swelling, persistent abdominal pain, neurological symptoms like blurry vision and blood spots under the skin beyond the site of injection. If you have these symptoms, seek medical assistance.
April 9: Out of 34 million recipients of the vaccine, 222 have reported blood clots. They appear to be more likely in younger patients, but it’s otherwise impossible to predict who will experience them. Some experts say they can be treated with intravenous immune globulin, which is currently used to treat immune disorders along with some types of blood thinners.
June 9: A study in Nature Medicine suggests that there may be a very slightly elevated risk of blood disorders after receipt of the AstraZeneca vaccine, but not Pfizer’s. The study was based on an analysis of medical records in Scotland. Researchers say the vaccine’s benefits still outweigh the risks and that their results should not alter policy. The rates are similar to those seen with other common vaccines.
August 22: Researchers published two case studies of patients experiencing neurological effects such as losing balance and non-epileptic convulsions after the Pfizer and AstraZeneca vaccines. They emphasize that functional neurological disorders are treatable.
Dec 8: The FDA authorized Astrazeneca’s monoclonal antibody treatment as an alternative to the vaccine for people over 12 years old who are immunocompromised or have a history of severe vaccine reactions. The treatment is given in two injections and protection is thought to last 6 months up to a year. It reduced the risk of symptomatic COVID-19 by 82%.
Novavax began Phase III clinical trials with its vaccine candidate in the United Kingdom in September and is had planned to start a trial in the United States in October. The trial was delayed due to manufacturing problems. The U.S. trial started on December 28. During Phase I/II trials, patients reported adverse events similar to those of other vaccine candidates, including injection site pain, rash, headaches, muscle pain, fever, nausea and vomiting.
June 14: Novavax announced promising efficacy data in a press release. The release suggested that the vaccine has similar side effects to others already approved, but that they may be slightly milder. Complete data is not yet available.
In July, Sinopharm launched Phase III trials of its two vaccine candidates in the United Arab Emirates, Peru, Morocco, and Argentina, which are now approved for limited use in healthcare workers in China and the UAE. In earlier trials of one of the vaccines, made in collaboration with Wuhan Institute of Biological Products, about 15% of the patients reported adverse events similar to those of other vaccine candidates, including injection site pain, rash, headaches, muscle pain, fever, nausea and vomiting. There is little data available about the second vaccine, made in collaboration with the Beijing Institute of Biological Products.
Sinovac opened Phase III trials of its vaccine candidate, CoronaVac, in July. It is already being used with emergency approval for high risk individuals in China. The earlier trials showed that about a third of patients experienced adverse effects similar to those in other vaccine candidates like injection site pain, fever, and fatigue, but the study included few details about more specific symptoms like nausea, headaches, and vomiting. On November 10, the trial was halted in Brazil due to a participant’s death. However, researchers say the death was not vaccine-related and the trial should continue. It has not been halted in other countries.
The Murdoch Children’s Research Institute is running a Phase III trial repurposing Bacillus Calmette-Guerin — a vaccine developed nearly a century ago to prevent tuberculosis infections — to prevent Covid-19. Since the vaccine has been around such a long time, there are many reports on its potential adverse effects and the vaccine itself has been altered to minimize many of them. Injection site reactions are common, and lymphadenitis, swelling of the lymph nodes, is common.
Bharat Biotech announced it would begin Phase III trials in India on October 23. In early trials demonstrated side effect profiles similar to those of the other vaccines, including pain at the injection site, fatigue, headache, and fever. The country announced emergency approval, though no Phase III data was included in the announcement.

If you’ve experienced side effects or medication issues related to this topic, we want to hear from you.
Submit Your StoryDISCLAIMER: MedShadow provides information and resources related to medications, their effects, and potential side effects. However, it is important to note that we are not a substitute for professional medical advice, diagnosis, or treatment. The content on our site is intended for educational and informational purposes only. Individuals dealing with medical conditions or symptoms should seek guidance from a licensed healthcare professional, such as a physician or pharmacist, who can provide personalized medical advice tailored to their specific circumstances.
While we strive to ensure the accuracy and reliability of the information presented on MedShadow, we cannot guarantee its completeness or suitability for any particular individual’s medical needs. Therefore, we strongly encourage users to consult with qualified healthcare professionals regarding any health-related concerns or decisions. By accessing and using MedShadow, you acknowledge and agree that the information provided on the site is not a substitute for professional medical advice and that you should always consult with a qualified healthcare provider for any medical concerns.

Help fund our fight for improved medication safety and transparency by supporting our independent journalism.
Give NowWe seek to create a world where there are safer medications for all and where all people are fully informed about their medication benefits and side effects, using our explanatory and investigative journalism to both inform and stimulate public discussion to drive toward solutions.
Stream our library on demand, including insights on generic drugs and pain management, straight from experts.
WATCH NOW DaveNovember 21, 2021 2:36 PM
https://doi.org/10.1186/s40249-021-00915-3
“The study also reported overall pooled incidence rate was 1.5% for adverse events, 0.4 per 10,000 for severe adverse events, and 0.1 per 10 000 for DEATH after vaccination.
Healthcare workers showed a higher incidence rate for adverse events, serious adverse events, as well death after vaccination. Also, the incidence rate of adverse events was found to be higher in the AZD1222 vaccine group, serious adverse events were found to be higher in the Gam-COVID-Vac vaccine group, and DEATH after vaccination was found to be higher in the BNT162b2 vaccine group.”
So basically, if a high school has a thousand students, if you immunize everyone at one hundred schools, 1 person will die.
And more deaths occur when the Pfizer-Biotech vaccine is used.
Adverse side effects affect more than 1 out of each 100 vaccinated.
 JakeNovember 26, 2021 3:34 AM
This is from the same study you put up “Our meta-analysis still has several limitations. First, we may include limited basic data on specific populations, as vaccination is slowly being promoted in populations under the age of 18 or over 60. Second, due to the limitation of the original real-world study, we did not conduct subgroup analysis based on more population characteristics, such as age. When analyzing the efficacy and safety of COVID-19 vaccine, we may have neglected the discussion on the heterogeneity from these sources. Third, most of the original studies only collected adverse events within 7 days after vaccination, which may limit the duration of follow-up for safety analysis”
n terms of adverse events after vaccination, the pooled incidence rate was very low, only 1.5% (95% CI: 1.4–1.6%). However, the prevalence of adverse events reported in large population (population size > 100 000) was much lower than that in small to medium population size. On the one hand, the vaccination population in the small to medium scale studies we included were mostly composed by health care workers, patients with specific diseases or the elderly. And these people are more concerned about their health and more sensitive to changes of themselves. But it remains to be proved whether patients or the elderly are more likely to have adverse events than the general.
U.S. mortality rate for covid19 1.6%
https://coronavirus.jhu.edu/data/mortality
Looks like incidence of death is higher with covid19 vs vaccine
DaveNovember 2, 2021 3:10 PMhttps://www.news-medical.net/news/20211101/Large-US-study-finds-majority-of-mRNA-COVID-19-side-effects-are-mild-and-temporary.aspx
The latest analysis of 299 million covid vaccine doses and the VAERS side effects database shows:
1. 6.6% get severe side effects
2. 1.3% die
Crunch the numbers and depending on if you estimate based on 1-dose or 2-doses, you get:
Every 1 in 34000 to 68000 people getting covid vaccines die.
This is the size of a large university like UCLA. IE. Give every student at one such campus vaccines, 1 will die.
Every 1 in 6700 to 13000 people getting covid vaccines experience severe side effects.
This is the size of a community college. Ie. Give everyone on campus this size the vaccine, 1 will get very sick.
3. A significant number of those dying after vaccination are the elderly.
It’s not clear if simply going to get the vaccination (not distancing) exposed them to the covid or not either. Ie. Those distancing at home tend to be the least exposed, but medical professionals giving vaccinations tend to be the most exposed to covid infection since they’re around many potentially infected people daily. So simply going out for a vaccine can increase odds greatly vs distancing at home and having everything delivered.
DaveOctober 25, 2021 3:12 PMhttps://medicalxpress.com/news/2021-10-teens-covid-sudden-severe-psychiatric.html
Not enough data to determine if this is limited to actual covid infection or includes vaccines or mitigated by vaccines, but is a heads up in case anyone you know goes nuts suddenly.
“Suicidal thoughts, “paranoia-like fears,” delusions and “foggy brain” have been identified in three adolescents who had mild or asymptomatic COVID-19. ”
“
DaveOctober 21, 2021 4:07 PMhttps://www.medrxiv.org/content/10.1101/2021.10.14.21265010v1
Out of almost 7000 who got the vaccines (any of the 3 – Pfizer, Moderna, J&J).
Hospitalization 0.3% and severe allergic reactions 0.6%. (Very roughly 1 in 1000 and 1 in 2000, with 1000-2000 people the population of some high schools.)
Those with autoimmune disease or lung disease were approximately twice as likely to seek medical care.
 TatianaOctober 10, 2021 11:34 AM
Please watch this press conference. Ex famous football player and his wife are helping those who need a voice in this. I will list the link here of the televised press conference with Senator Johnson and also the organization you can contact privately to voice your concerns:
https://youtu.be/6mxqC9SiRh8
https://www.c19vaxreactions.com
I hope this information is useful in gaining understanding and helping us all along with this extremely complex situation.
 SabaOctober 5, 2021 5:20 PM
I wanted to come back here and post a positive story about insomnia issues after the vax. You can see my previous posts of desperation from back in March. 42 y/o male, with no health issues prior to vax. Rather I was very athletic and best shape ever. First and only Moderna on 03/19/21. Did not take the 2nd shot due to the side effects. I had severe insomnia starting the next night. It is hard to describe the hell I went through because of insomnia for almost over 5 months. Nothing, even rx meds didn’t work, especially the first 3-4 months. It only started to show slow improvements around the 4-month mark, much better at the 5-month mark. I am over 6 months now and while I am still not sleeping like pre-vax, my sleep is mostly back where I can get 6 hours of sleep. I may still wake up once but don’t struggle to go back. Sleeping anything over 6 hours, especially early morning. I know of another person that went through the same and it took him 5-6 months as well. He is 8 months out now and fully recovered. With the slow progress I have seen, I am sure I will get there. Anyone new to this issue, be calm, it will get better. It may take weeks/months, but it will eventually get better. I still have tinnitus 6 months out that while not as bad, still can be bothersome early morning. I have seen some reports that it went away so I am still hopeful. And I am also dealing with floaters in my eyes which by far are the most bothersome after insomnia. They say they can be permanent and your brain does tune them out. 4 months out since their onset, I am still struggling. Anyway, this post was mainly for anyone with insomnia issues and to give them hope.
 CoriDecember 6, 2021 12:13 PM
It likely would have been a lot better to get covid than the side effects you experienced from the vaccine.
 JackOctober 3, 2021 3:56 AM
4 months in from first jab of Moderna and struggling with my chest and unable to sleep at night. Any kind of physical activity triggers a chest pain as if I had fragments of glass inside. At night, anxiety hits me and unable to get any sleep and if I do I worry that I’ll even wake up the next day.
DaveOctober 2, 2021 4:16 PM“A one-dose Moderna vaccine had the highest antibody titers compared to all three vaccines.”
This reflects the fact that Moderna has been reported to contain a “higher amount of active ingredient in the Moderna vaccine — 100 micrograms, versus 30 micrograms in Pfizer”.
SO, if one must get the vaccine, Moderna would provide the best protection regardless of what side effects vaccines create.
DaveSeptember 30, 2021 9:19 PMWe found that 1095 patients (45.0%) reported at least 1 symptom, and the most common symptoms were fatigue, sweating, chest tightness, anxiety, and myalgia. Older age, female gender, and severe disease were associated with higher risks of fatigue or more symptoms. In total, 161 patients (6.6%) had CAT total scores of at least 10, for which the risk factors included severe disease during hospital stay or coexisting cerebrovascular diseases.
https://jamanetwork.com/journals/jamanetworkopen/fullarticle/2784558
Would be interesting to see what percentage of the vaccinated but never infected get long term side effects.
DaveSeptember 30, 2021 9:17 PMJAMA Network Open
full text iconFULL TEXTcontents iconCONTENTSfigure iconFIGURES /
TABLESattach iconSUPPLEMENTAL
CONTENTreferences iconREFERENCESrelated iconRELATEDcomments iconCOMMENTS
Download PDF
Comment
Top of Article
Key Points
Abstract
Introduction
Methods
Results
Discussion
Conclusions
Article Information
References
Figure 1. Study Flowchart
Study Flowchart
Figure 2. Total and Item CAT Scores in Patients at 1-Year Follow-up
Total and Item CAT Scores in Patients at 1-Year Follow-up
ADL indicates activities of daily living; CAT, COPD assessment test; COPD, chronic obstructive pulmonary disease.
Table 1. Characteristics of Enrolled Patients
Characteristics of Enrolled Patients
Table 2. Symptoms at 1-Year Follow-up According to Disease Severity
Symptoms at 1-Year Follow-up According to Disease Severity
Table 3. Logistic Regression Models to Evaluate the Risk Factors for CAT Scores ≥10
Logistic Regression Models to Evaluate the Risk Factors for CAT Scores ≥10
1.
2.
3.
4.
5.
6.
7.
8.
9.
10.
11.
12.
13.
14.
15.
16.
17.
18.
19.
20.
21.
22.
23.
24.
25.
26.
27.
28.
29.
30.
31.
32.
33.
34.
COVID-19 Resource Center
See More About
Global Health Coronavirus (COVID-19) Psychiatry and Behavioral Health Infectious Diseases Chronic Obstructive Pulmonary Disease Pulmonary Medicine
open access
Sign Up for Emails Based on Your Interests
Others Also Liked
Asthma-COPD overlap strong risk factor for COVID-19 hospitalization
Healio
Lo studio identifica i fattori associati all’ARDS in COVID-19
Healio
Incidence of symptomatic, image-confirmed venous thromboembolism following hospitalization for COVID-19 with 90-day follow-up
Richard Salisbury et al., Blood Advances, 2020
Powered by
Comment
This Issue
Views 2,207 Citations 0
127
PDF
Original Investigation Global Health
September 29, 2021
Symptoms and Health Outcomes Among Survivors of COVID-19 Infection 1 Year After Discharge From Hospitals in Wuhan, China
Xue Zhang, BS1; Fang Wang, BS1; Ye Shen, MS1; et alXiaohua Zhang, MD2,3; Yuan Cen, MS3,4; Bin Wang, MD3,5; Songtao Zhao, MD3,6; Yi Zhou, MD3,7; Baoman Hu, BS1; Man Wang, BS1; Yuhui Liu, MD8; Hongming Miao, MD9; Paul Jones, MD10; Xiangyu Ma, MD11; Yong He, MD1; Guoqiang Cao, MD1,3; Lixia Cheng, MS12,13; Li Li, MD1,3
Author Affiliations Article Information
JAMA Netw Open. 2021;4(9):e2127403. doi:10.1001/jamanetworkopen.2021.27403
COVID-19 Resource Center
Key Points
Question What are the long-term health outcomes associated with COVID-19 infection 1 year after hospital discharge?
Findings In this cohort study of 2433 patients who had been hospitalized with COVID-19, the most common symptoms at 1 year after discharge were fatigue, sweating, chest tightness, anxiety, and myalgia. Patients with severe disease had more postinfection symptoms and higher chronic obstructive pulmonary disease assessment test scores.
Meaning This study reported prolonged symptoms of COVID-19 and found that severe disease during hospitalization was a risk factor for more symptoms and higher chronic obstructive pulmonary disease assessment test scores.
Abstract
Importance The long-term health outcomes and symptom burden of COVID-19 remain largely unclear.
Objective To evaluate health outcomes of COVID-19 survivors 1 year after hospital discharge and to identify associated risk factors.
Design, Setting, and Participants This retrospective, multicenter cohort study was conducted at 2 designated hospitals, Huoshenshan Hospital and Taikang Tongji Hospital, both in Wuhan, China. All adult patients with COVID-19 discharged between February 12 and April 10, 2020, were screened for eligibility. Of a consecutive sample of 3988 discharged patients, 1555 were excluded (796 declined to participate and 759 were unable to be contacted) and the remaining 2433 patients were enrolled. All patients were interviewed via telephone from March 1 to March 20, 2021. Statistical analysis was performed from March 28 to April 18, 2021.
Exposures COVID-19.
Main Outcomes and Measures All patients participated in telephone interviews using a series of questionnaires for evaluation of symptoms, along with a chronic obstructive pulmonary disease (COPD) assessment test (CAT). Logistic regression models were used to evaluate risk factors for fatigue, dyspnea, symptom burden, or higher CAT scores.
Results Of 2433 patients at 1-year follow-up, 1205 (49.5%) were men and 680 (27.9%) were categorized into the severe disease group as defined by the World Health Organization guideline; the median (IQR) age was 60.0 (49.0-68.0) years. In total, 1095 patients (45.0%) reported at least 1 symptom. The most common symptoms included fatigue, sweating, chest tightness, anxiety, and myalgia. Older age (odds ratio [OR], 1.02; 95% CI, 1.01-1.02; P < .001), female sex (OR, 1.27; 95% CI, 1.06-1.52; P = .008), and severe disease during hospital stay (OR, 1.43; 95% CI, 1.18-1.74; P < .001) were associated with higher risks of fatigue. Older age (OR, 1.02; 95% CI, 1.01-1.03; P < .001) and severe disease (OR, 1.51; 95% CI, 1.14-1.99; P = .004) were associated with higher risks of having at least 3 symptoms. The median (IQR) CAT score was 2 (0-4), and a total of 161 patients (6.6%) had a CAT score of at least 10. Severe disease (OR, 1.84; 95% CI, 1.31-2.58; P < .001) and coexisting cerebrovascular diseases (OR, 1.95; 95% CI, 1.07-3.54; P = .03) were independent risk factors for CAT scores of at least 10.
Conclusions and Relevance This study found that patients with COVID-19 with severe disease during hospitalization had more postinfection symptoms and higher CAT scores.
Introduction
COVID-19 has spread rapidly into a global pandemic ever since the initial reports in December 2019 in China, which has caused millions of deaths.1 The disease affects multiple systems of the body in the acute phase, represented by acute pneumonia.2 With the increasing number of patients recovered, postinfection health consequences have been recognized.3-5 The first survivors in Wuhan, China, have now lived for 1 year, which provides an opportunity to address the long-term sequelae of COVID-19 in a large population sample.
Several studies have reported that COVID-19 survivors might have persistent symptoms, impaired lung function, and chest imaging abnormalities.5-9 At 6 months after symptom onset, 76% of patients reported at least 1 symptom, the most common being fatigue, muscle weakness, and sleep difficulties.10 In a prospective cohort study of 83 patients with COVID-19, dyspnea scores and exercise capacity improved at 1 year after hospital discharge, whereas radiological changes persisted in 20 (24%) patients.11 In another study of COVID-19 survivors 1 year after hospital discharge, post–COVID-19 symptoms included fatigue, dyspnea, chest pain, and cough.12 There are currently no agreed-upon measures to assess the symptom burden of COVID-19. However, the Chronic Obstructive Pulmonary Disease (COPD) Assessment Test (CAT), an 8-item questionnaire designed to quantify health status impairment in COPD patients,13 demonstrated a high CAT score in patients with COVID-19 in the weeks following their admission.14 However, the long-term symptom burden and health outcomes remain largely unknown. This study aimed to determine the long-term health outcomes associated with COVID-19 in a group of patients discharged from 2 designated hospitals of Wuhan one year after discharge.
Methods
This cohort study was approved by the Ethics Committee of the Daping Hospital of Army Medical University and registered at the Chinese Clinical Trial Registry (ChiCTR2100045964). Verbal informed consent was obtained from all participants or their legal guardians prior to the survey. The study followed the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) reporting guideline.
Study Design and Patients
All adult patients with laboratory-confirmed COVID-19 who were discharged from Huoshenshan Hospital and Taikang Tongji Hospital (both in Wuhan, China) between February 12 and April 10, 2020, were screened for eligibility. The follow-up study was conducted from March 1 to March 20, 2021. All discharged patients met uniform discharge criteria according to the Chinese clinical guidance for COVID-19 pneumonia diagnosis and treatment issued by the National Health Commission.15 The exclusion criteria included (1) those who declined to participate and (2) those unable to be contacted.
Procedures and Data Acquisition
All patients were contacted in the order of their discharge date as documented in the medical record. Patients were interviewed via telephone by trained physicians using a series of questionnaires, including a self-reported symptom questionnaire, and CAT, as shown in eTable 1 in the Supplement. A CAT score of at least 10 is recommended as the threshold for maintenance treatment in COPD,16 which was based on a modeling study of the association between CAT scores and the daily life and well-being patients with COPD.17 The symptom questionnaire was based on symptoms that had been reported by patients during hospitalization, which was described in an earlier study.18 These symptoms included fever, cough, fatigue, anorexia, shortness of breath, chest tightness, myalgia, expectoration, dyspnea, diarrhea, sore throat, nausea, vomiting, headache, chill, dizziness, and hemoptysis. Patients were asked to report any persistent or newly occurring symptoms. The patients' current symptoms were carefully distinguished from those of their preillness state or other underlying diseases not related to COVID-19.
Clinical data for patients during hospitalization were retrieved from electronic medical records, including demographic characteristics (self-reported race, age, sex, and cigarette smoking) and clinical characteristics (self-reported comorbidities, symptoms, and chest images). The disease severity was defined by World Health Organization guideline for COVID 19.19 Severe pneumonia refers to fever or suspected respiratory infection, plus 1 of the following: respiratory rate greater than 30 breaths per minute; severe respiratory distress; or oxygen saturation as measured by pulse oximetry (SpO2) less than or equal to 93% on room air.19 We double-entered and validated all data using EpiData software version 3.1 (EpiData Association).
Statistical Analysis
Continuous variables were described as median with IQR, followed by Mann-Whitney U test. Categorical variables were presented as absolute values along with percentages and compared using the Pearson χ2 test or Fisher exact test. We compared the clinical characteristics between enrolled patients and those who were lost to follow-up. To test for the risk of bias due to the patients who were lost to follow-up, 1:1 propensity score–matching between the subpopulation lost to follow-up (n = 1555) and the enrolled subpopulation (n = 2433) was carried out. To explore factors associated with the risk of fatigue, dyspnea, occurrence of at least 3 symptoms, and CAT scores of at least 10, univariate logistic regression analysis was used to identify potential risk factors with P < .10. These were then used in a stepwise (forward:LR) selection process in multivariate logistic regression model. All tests were 2-sided, and P < .05 was considered statistically significant. All statistical analyses were performed with the use of R software version 3.6.2 (R Project for Statistical Computing) from March 28 to April 18, 2021.
Results
Patient Characteristics
A total of 3988 COVID-19 survivors were screened for eligibility. In total, 1555 patients were excluded (796 declined to participate and 759 were unable to be contacted) and the remaining 2433 patients were enrolled for the questionnaire phone interview (Figure 1). Among the patients who were enrolled, 1205 (49.5%) were men, 1228 (50.5%) were women, and 680 (27.9%) were categorized as having severe disease; the median (IQR) age of the enrolled patients was 60.0 (49.0–68.0) years. The most common comorbidity was hypertension (712 patients [29.3%]). The median (IQR) duration of hospital stay was 14.0 (9.0-20.0) days, and the median (IQR) time from discharge to follow-up was 364.0 (357.0–371.0) days. During hospitalization, 54 patients (2.2%) were admitted to the intensive care unit (ICU). In total, 1743 patients (71.6%) received oxygen therapy, among which 21 patients (0.9%) received mechanical ventilation. Patients in the severe group were older, had more male individuals, had higher frequencies of coexisting disorders, and had a longer hospital stay, as well as a higher percentage of ICU admission (Table 1).
Compared with enrolled patients, those who were lost to follow-up (N = 1555) were older, had a higher percentage of co-existing hypertension, cardiovascular diseases, cerebrovascular diseases and COPD, and had a higher percentage of ICU admission and mechanical ventilation. No significant difference was found in sex, disease severity, or the percentage of smokers (Table 1).
Characteristics of Long-term Sequelae at 1-Year Follow-up
During hospitalization, 2322 out of 2433 patients (95.4%) reported at least 1 symptom. At 1-year follow-up, 1338 patients (55.0%) were completely free of any COVID-19–related symptom, whereas 1095 patients (45.0%) reported at least 1 symptom, and the percentage was higher in the patients who were in the severe group while hospitalized (severe vs nonsevere: 54.0% vs 41.5%; OR, 1.31 [95% CI, 1.04-1.65]; P = .02). Female patients had a higher percentage of any symptoms than male patients (female vs male: 47.9% vs 42.1%; OR, 0.81 [95% CI, 0.65-1.00]; P = .049). Of those with persisting symptoms, 412 (16.9%) reported 1 symptom, 299 (12.3%) reported 2 symptoms, and 384 (15.8%) reported 3 or more symptoms.
During hospitalization, the most common symptoms were fever (77.2% [1878 patients]), cough (70.0% [1703 patients]), fatigue (55.3% [1345 patients]), anorexia (50.6% [1232 patients]), and shortness of breath (41.1% [1000 patients]) (eTable 2 in the Supplement). At 1-year follow-up, no patient reported fever and the most common symptoms were fatigue (27.7% [696 patients]), sweating (16.9% [424 patients]), chest tightness (13.0% [326 patients]), anxiety (10.4% [262 patients]), and myalgia (7.9% [198 patients]) (Table 2). The percentage of symptoms during the acute phase of the disease and at 1-year follow-up is compared in the eFigure in the Supplement. The percentage of patients reporting cough decreased to 4.1% [104 patients], anorexia to 0.8% [20 patients], and shortness of breath to 4.1% [103 patients]. Besides sweating and anxiety, there were several other newly reported symptoms, including palpitation (4.2% [106 patients]), edema of lower limbs (1.4% [36 patients]), taste change (1.4% [35 patients]), and impaired sense of smell (1.3% [32 patients]). The prevalence of several symptoms in the severe group was significantly higher than those in the nonsevere group (severe vs nonsevere fatigue: 35.9% vs 25.8%; OR, 1.36 [95% CI, 1.10-1.68]; P = .004; severe vs nonsevere chest tightness: 20.4% vs 10.7%; OR, 1.68 [95% CI, 1.29-2.19]; P < .001; severe vs nonsevere shortness of breath: 6.6% vs 3.3%; OR, 1.84 [95% CI, 1.17-2.88]; P = .008; severe vs nonsevere impaired sense of smell: 2.5% vs 0.9%; OR, 2.59 [95% CI, 1.19-5.65]; P = .02; severe vs nonsevere sore throat: 1.8% vs 0.7%; OR, 3.10 [95% CI, 1.31-7.32]; P = .01). Female patients had significantly higher percentages of anxiety (13.4% vs 8.1%, P = .001), myalgia (9.6% vs 6.6%, P = .01), and headache (3.1% vs 1.6%, P = .001) (eTable 3 in the Supplement).
After propensity score–matching, 1453 patients (59.7%) in the enrolled population were matched successfully with those lost to follow-up. As shown in eTable 4 in the Supplement, the baseline characteristics were comparable. In the propensity score–matched population, the most common symptoms were fatigue (29.2% [425 patients]), sweating (16.7% [243 patients]), chest tightness (13.4% [195 patients]), anxiety (10.7% [155 patients]), and myalgia (8.5% [124 patients]), which were similar to that of the overall enrolled population (eTable 5 in the Supplement).
Risk Factors of Post-Infection Sequelae at 1-Year Follow-up
We next investigated risk factors for fatigue, which was the most common symptom at 1-year follow-up (eTable 6 in the Supplement). On univariate analysis, age, sex, disease severity, oxygen therapy, mechanical ventilation, length of hospital stay, and follow-up times were associated with fatigue. After multivariable adjustment, severe disease (OR, 1.43; 95% CI, 1.18-1.74; P < .001), older age (OR, 1.02; 95% CI, 1.01-1.02; P < .001), and female sex (OR, 1.27; 95% CI, 1.06-1.52; P = .008) were associated with a higher risk of fatigue. For dyspnea, age, oxygen therapy, mechanical ventilation, and coexisting chronic liver diseases were risk factors after multivariable adjustment (eTable 7 in the Supplement).
In patients with at least 3 symptoms at 1-year of follow-up, older age (OR, 1.02; 95% CI, 1.01-1.03; P < .001) and severe disease (OR, 1.51; 95% CI, 1.14-1.99; P = .004) were independent risk factors (eTable 8 in the Supplement).
CAT Scoring at 1-Year Follow-up
Previously, CAT was shown to be a useful tool to assess symptom burden of patients with COVID-19.14 In the present study, all 2433 patients completed CAT assessment. The median (IQR) CAT score was 2 (0–4) in the total cohort, and the severe group had a significantly higher median (IQR) CAT score ( 2 [0–5]) compared with the nonsevere group (1 [0–3]; P < .001) (Figure 2A). A total of 161 patients (6.6%) had CAT total scores of at least 10. The severe group had a significantly higher proportion of patients with a CAT score of at least 10 compared with the nonsevere group (severe vs nonsevere: 79 [11.6%] vs 82 [4.7%]; χ2=38.187; P < .001) (Figure 2B). The CAT item scores are shown in Figure 2C.
We next assessed risk factors associated with CAT scores of at least 10. On univariate analysis, severe disease (OR, 2.68; 95% CI, 1.94-3.71; P < .001), ICU admission (OR, 2.93; 95% CI, 1.40-6.10; P = .004), mechanical ventilation (OR, 3.59; 95% CI, 1.19-10.85; P = .02), hypertension (OR, 1.66; 95% CI, 1.20-2.31; P = .002), cardiovascular diseases (OR, 2.36; 95% CI, 1.54-3.62; P < .001), and cerebrovascular diseases (OR, 3.80; 95% CI, 2.14-6.74; P < .001) were associated with higher odds of CAT scores of at least 10. After multivariable adjustment, severe disease (OR, 1.84; 95% CI, 1.31-2.58; P < .001), and coexisting cerebrovascular diseases (OR, 1.95; 95% CI, 1.07-3.54; P = .03) were found to be independent risk factors for CAT scores of at least 10 (Table 3).
Discussion
This study reports the long-term health outcomes of COVID-19 survivors at 1-year after hospital discharge in a large cohort of patients. We found that 1095 patients (45.0%) reported at least 1 symptom, and the most common symptoms were fatigue, sweating, chest tightness, anxiety, and myalgia. Older age, female gender, and severe disease were associated with higher risks of fatigue or more symptoms.
https://jamanetwork.com/journals/jamanetworkopen/fullarticle/2784558
For those who don't get vaccinated, 45% of those infected in this 1 year study had long term side effects.
Naturally, it'll be interesting to see what percentage of the vaccinated but not infected get long term side effects.
 ConcernedVaxxerSeptember 22, 2021 8:24 PM
5 days after getting the 1st dose of the Pfizer vaccine I developed swelling, bruising, pain and redness in my breast. There is a large area of very dark bruising, swollen lymph nodes that are raised and visible through the skin and tenderness to the touch. The symptoms are only in my left breast which is the same side I had the vaccine injection (left arm). It’s been almost two months and I still have daily breast pain, bruising and minor swelling in the left breast. My doctor gave me Prednisone and the symptoms went away while I was taking the meds. However, they reoccurred 2 days after I finished the 6-day round of steroids. There were actually more red, swollen lymph nodes afterwards. My doctor said she had never seen anything like this and has scheduled me for diagnostic testing.
 DavidSeptember 17, 2021 10:42 PM
Report your adverse reaction to the vaccine at the VAERS website: https://vaers.hhs.gov/reportevent.html
I myself took the second dose of Moderna back on April 30. Four days later I began to experience heart palpitations / skipped heart beats that lasted for months. My primary care physician and a different cardiologist told me they didn’t think the vaccine was the direct cause (yeah, right). Anyway, I got myself on magnesium citrate and the palpitations have thankfully gone away.
 RobertSeptember 10, 2021 1:46 PM
I don’t claim any medical knowledge. I’ve not taken the vaccines and don’t intend to. But I have a question and hope it’s answerable.
My wife’s 63 year old brother, in the Philippines, very healthy person, got his second dose of Pfizer two days ago.
He collapsed there in the clinic and was rushed to the hospital. He has no history of any medical issues.
Sadly, his kidneys had immediately started shutting down and he died less than two days later.
I’m not looking for pro or anti vaxx arguments, I respect whatever you choose for yourself and feel that’s how it should be.
I just want to know. medically, how in the world can this happen to a guy who’s healthy as can be and climbs mountains every week?
What in that vaccine could have caused that? I’m not aware of any instances of kidney issues in my wife’s family. She said there are none.
Thank you.
 RhondaSeptember 10, 2021 11:26 PM
I have no information other than my deepest condolences. This is not the first time I have heard of this happening, however, and unless an autopsy is performed, and sent to the appropriate people, you may never know. This doctor in the US studies tissue samples of those who died after the jab. You may want to get in touch with him: https://independentdocsid.com/RyanColeMD?fbclid=IwAR23adZjV401ooT4Lk_4jh-KQbo0NnijrCJxxwi25kQhc5jGK5eH1wGHUuk
 Janice R HuguetSeptember 10, 2021 8:35 PM
The adjuvant in these vaccines is squalene if you had read Gary Matsumoto’s book Vaccine A, I would be very hesitant to take this vaccine.
DaveSeptember 10, 2021 5:36 PMhttps://www.webmd.com/lung/covid-kidneys-damage-coronavirus
https://www.reuters.com/business/healthcare-pharmaceuticals/severe-kidney-problems-seen-with-covid-19-second-vaccine-dose-should-not-be-2021-03-12/
European medicines agency:
“Glomerulonephritis and nephrotic syndrome
PRAC started an assessment of glomerulonephritis (inflammation of tiny filters in the kidneys) and nephrotic syndrome (kidney disorder causing the kidneys to leak too much protein in the urine) to establish whether they may be side effects of Comirnaty. Affected patients may present with bloody or foamy urine, oedema (swelling of the eyelids, feet or abdomen),
1 The European Centre for Disease Prevention and Control (ECDC) collects these exposure data from EU Member States as well as from the additional countries of the European Economic Area (EEA) Norway, Iceland and Liechtenstein. 2 Monthly Summary Safety Reports, also referred to as pandemic summary safety reports, will be compiled by the marketing authorisation holders to support timely and continuous benefit-risk evaluations for COVID-19 vaccines used during the pandemic. These reports complement the submission of Periodic Safety Update Reports (PSURs). The assessment follows a small number of cases reported after vaccination with Comirnaty in the medical literature, including cases where patients experienced relapse of pre-existing kidney conditions.
Further data and analyses have been requested from the marketing authorisation holder to support the ongoing assessment by PRAC.”
…
The mRNA vaccines generate proteins that trigger a response by the human body as if the covid virus was present.
While it is not the full virus, the proteins can trigger responses similar to an actual infection, not only from the immune system, but in other systems and organs as well.
The 50,000 step process as documented by Time magazine for Pfizer is also brand-new and created specifically to make the new mRNA vaccine and has never been fully validated or tested before for commercial mRNA production. In fact, 2019, no mRNA vaccine reached beyond stage ii clinical trials.
So, you can imagine that it is likely not all the mRNA triggered proteins are exactly the proteins intended to be produced due to manufacturing errors, and can also trigger other, unintended responses.
In any case, the covid virus itself seems to cause kidney damage in some patients, so it’s possible that the proteins from the mRNA vaccinations are leading to the same.
 Emma YasinskiSeptember 10, 2021 3:02 PM
There’s a brief mention of a possible association between vaccination and glomerular disease here: https://www.uptodate.com/contents/covid-19-issues-related-to-acute-kidney-injury-glomerular-disease-and-hypertension/print?search=covid%2019&source=covid19_landing&usage_type=main_section
Here is a brief discussion of acute kidney failure (in general, not in the context of vaccination) https://www.kidney.org/news/kidneyCare/winter10/KidneyFunction
DaveSeptember 8, 2021 10:54 PMhttps://www.yahoo.com/news/pfiizer-picked-covid-19-vaccine-125332549.html
“Pfizer’s top scientist said it chose a relatively low COVID-19 vaccine dose to minimize side effects.
Pfizer’s vaccine has 30 micrograms of mRNA, the active ingredient. Moderna’s has 100 micrograms.”
Or…… Pfizer is giving us less than 1/3rd the ingredients needed for great protection, or Moderna is gonna cause us lots more side-effects….
Vaers does report More Moderna events than Pfizer events, supporting this (more Pfizer doses given).
https://wonder.cdc.gov/
That said, the latest data shows an increased risk of Heart Problems after Pfizer/Moderna vaccination, so those with current heart disease should weigh the pros and cons.
DaveSeptember 10, 2021 5:21 PMhttps://medicalxpress.com/news/2021-09-vaccines-effective-delta-variant.html
On the flip side, with Moderna having more than 3x the active ingredients than Pfizer, its effectiveness against the Delta strain is much better should one decide to get vaccinated:
“Moderna was 95 percent effective at preventing hospitalizations among adults ages 18 and older.
Pfizer was 80 percent effective at preventing hospitalizations among adults ages 18 and older.
Johnson & Johnson was 60 percent effective at preventing hospitalizations among adults ages 18 and older. ”
“
DaveSeptember 5, 2021 6:00 PMhttps://doi.org/10.1056/NEJMoa2110475
Data from 2.4 million vaccinated Israelis show that the “Pfizer” vaccine have these side-effects:
“In short, the study has shown that vaccination was strongly associated with an increased risk of myocarditis (2.7 events per 100,000 persons), as well as lymphadenopathy (which occurred relatively frequent with 78.5 events per 100,000 persons), herpes zoster infection (which can translate to an increased risk of Bell’s palsy) and appendicitis.
On the other hand, SARS-CoV-2 infection was linked to a substantially elevated risk of myocarditis (11 events per 100,000 persons), alongside the risk of pericarditis, arrhythmia, pulmonary embolism, deep-vein thrombosis, myocardial infarction, thrombocytopenia, and intracranial hemorrhage.
The study has also shown that the risk of myocarditis is basically increased by a factor of three following vaccination. Furthermore, among the 21 persons with myocarditis in the group that received the vaccine, the median age was 25 years and there was a substantial male predominance.”
 AmySeptember 7, 2021 8:10 PM
Dave these articles are readily available on the internet, if googled. I am interested in knowing actual side effects not some studies posted on web. This page is a side effects tracker and people are not posting here anymore as they can only see your posts and are probably getting confused.
 JessicaSeptember 7, 2021 6:16 PM
This thing is so scary. I’m not sure how things are in other countries but in Australia we’ve been in lockdown and being told that unless we are fully vaccinated, we won’t be allowed to basically live. No restaurants, no travel, anything.. how the heck can they do that to us and we have no human rights? I’m very scared as I’m seeing people start getting covid but of the ones that are getting, I know one who’s been put into an induced coma. The others are either flu like or didn’t even know they had it.
I have been told that if you get it, you’re immune for 12mnths and won’t need the vaccines. Don’t think that’s true but either way I’m sooooo scared to still get this Pfizer 😭😭
 SamSeptember 3, 2021 9:12 AM
I had the Moderna shot just over two months ago and have suffered from burning tingling sensations all over my body, including some dizziness and light-headedness in the mornings off and on. Has anyone taken Gabapentin and if so, has it worked or have you needed to keep upping your dosage? What about natural treatments? Very frustrating and it’s waking me up all hours of the night,,,,, suggestions???
DaveSeptember 1, 2021 8:20 PMhttps://japantoday.com/category/national/moderna-says-tainted-covid-vaccines-sent-to-japan-contained-steel
Steel particles found in some batches of Moderna in Japan. Don’t be surprised if you got a jab with such batches and have side effects!
You can always ask the caregiver to visual check the vial for foreign particles prior to giving you a dose.
 SusieSeptember 3, 2021 10:07 PM
Thank you for your updates. I do not believe they are off topic.
amySeptember 2, 2021 7:12 PMPlease stop posting these articles, this is for people who have side effects
 SusanSeptember 3, 2021 11:21 PM
Amy can u please stop posting that Dave needs to stop. I find Dave’s comments interesting and useful.
Dave, please continue
 JaySeptember 1, 2021 3:25 PM
I will be waiting for Novavax approval here in Canada. The phase trials looked very good, and the amount of research and data available regarding protein sub unit vaccines is comforting. Also, I love how they are using an adjuvant sourced from a tree unlike from aluminum like post protein sub units have.
 thaiSeptember 13, 2021 3:42 AM
I’d like Novavax, too, but trouble our govt. has to first approve it in a process, then buy millions of doses. So far, U.S. govt. is buying millions of Pfizer doses and wants to use them up before buying anything else. I’ve also read that Novavax is lining up to sell it’s vax to less developed countries, due to ease of storage and Not to U.S. . Don’t know about Canada: are you sure your govt. will approve it and buy enough doses for all those who want it? I hope so!
JessAugust 30, 2021 9:36 AMHello!! I just wanted to get an update on how you guys are feeling. I’m in the Oz and as with most ppl, we are being forced to take the vaccine. My dr has advised me to take the Pfizer butbive had severe anxiety for the past few weeks thinking about the thought of taking it. I’ve had severe anxiety and panic attacks on the past to a point that I was admitted to hospital. I’m so so terrified that this vaccine may trigger these or if I can handle getting these again. My partner is booked to have his on Wednesday but I am severely scared that I’m certain I’ll make myself faint or collapse from how terrified I am
DaveSeptember 1, 2021 8:30 PMSee my “log” below.
1st shot nothing.
2nd shot dead for 3 days.
But agree with the above that efficacy has dropped to the annual flu shot level (60, 70%), if not lower versus certain, newer strains.
This means even after full vaccination, you can easily be the 1/3rd~ of infected cases (Los Angeles County data, etc) with a 1 in 100~ death rate after infection.
Gotta stay home, wear n95 or n100 masks, and stay away from others still to be safe.
…
That said, the vaccination do reduce the 80 year old chance of death (30%~+ after infection) to a 50 year old chance (8%~ or so), so for the elderly 50+ years, can be worth the risk of vaccination.
As for the young under 25, the annual flu kills more….
…
Easier to go through it with your partner so that you can see what side effects they have, then decide whether to go for it yourself.
…
Vaccination or not, covid is like sars/mers/flus in that not everyone dies, and some are resistant even after exposure. Some get 1 second of exposure and die, some get exposed all day for months and nothing happens. Most wind up in between like a bad flu if they show symptoms.
Thus far, in America, pfizer has the fewest reported manufacturing issues. J&J (dirty plant), Moderna (steel particles)…
 RedpillSeptember 1, 2021 9:01 AM
My heart goes out to you. All of the shots have adverse effects that continue to be ignored by our of government and the regulatory agencies that are supposed to protect the populations. All one needs to do is look at what is happening in Israel to see what the US has in store. Prizer’s own study that was submitted using Israel data recent reports from Israel’s Ministry of Health. In early July, they reported that efficacy against infection and symptomatic disease “fell to 64%.” By late July it had fallen to 39% where Delta is the dominant strain. This is very low. For context, the FDA’s expectation is of “at least 50%” efficacy for any approvable vaccine. Delta is not responsible for waning immunity because Pfizer’s preprint, RCT reporting “up to six months of follow-up,” it is notable that evidence of waning immunity was already visible in the data by the 13 March 2021 data cut-off. (https://www.cnbc.com/2021/07/23/delta-variant-pfizer-covid-vaccine-39percent-effective-in-israel-prevents-severe-illness.html). This is malpractice.
I believe this entire shot rollout and the machinations of the people behind it will go down in history just like what happened with the AIDS crisis as well as other medical/political blunders that will leave a stain on the history of the US and how it treated it’s citizens by trampling on their constitutional rights to Body Sovereignty and the Federal Law of Informed Consent.
DaveAugust 25, 2021 7:14 PMhttps://time.com/5955247/inside-biontech-vaccine-facility/
Don’t be too surprised if some of the side effects are due to manufacturing defects of the vaccines.
After all, any 50,000 step process created literally on-the-fly in 2020 and rushed out the door is bound to have a few things wrong.
The companies are improving the process over time, but any single error in a 50,000 step process can make a bad batch.
 ZeeAugust 26, 2021 10:03 PM
You always making excuses
